

Hi, I’m Sophia. If you’re aiming to lose 25 pounds, I want to start with the thing most articles on this topic skip: how fast you can safely do it matters as much as how you do it. Losing weight too aggressively backfires for most people — it’s harder to sustain, it costs you muscle along with fat, and it usually comes back. So let’s build a plan that’s realistic, evidence-based, and actually livable.
Updated October 2026 with new CDC and NIH guidance and a note on GLP-1 medications.
How fast can you safely lose 25 pounds?
This is the question behind most of the searches that bring people here — “losing 25 pounds a week,” “in a month,” “in 2 months” — so let’s answer it directly, because the honest answer is more useful than a dramatic promise.
| Timeline | Pace required | Realistic? |
|---|---|---|
| 25 pounds in 1 week | 25 lbs/week | No — not achievable or safe. This is mostly water weight if attempted, and dangerous if pursued through extreme restriction. |
| 25 pounds in 1 month | ~6 lbs/week | Not recommended. Requires an extreme deficit most people can’t sustain without losing significant muscle. |
| 25 pounds in 2 months | ~3 lbs/week | Aggressive. Possible for some people with a higher starting weight, but above the generally recommended pace. |
| 25 pounds in 3–4 months | 1.5–2 lbs/week | Realistic. Matches the CDC’s 1–2 lbs/week guidance. |
| 25 pounds in 5–6 months | ~1 lb/week | Very sustainable, easiest to stick with, minimal muscle loss. |
The CDC notes that people who lose weight at a gradual, steady pace of about 1 to 2 pounds a week are more likely to keep it off than people who lose it faster. At that pace, 25 pounds takes roughly 3 to 6 months. The CDC even uses “losing 20 pounds in 2 weeks” as its example of a goal that tends to leave people feeling defeated. Not the fast answer you were hoping for, I know. It’s the one that holds up, though.
One encouraging detail: you don’t have to hit 25 to feel a difference. The CDC points out that losing just 5% of your body weight (10 pounds if you weigh 200) can help improve blood pressure, cholesterol, and blood sugar.
What a realistic 25-pound plan looks like, month by month
Here’s roughly how it plays out at a steady 1–2 pounds a week. Your numbers will be different, and that’s normal. Water shifts, hormones, and stress all make the scale jumpy week to week.
| Phase | Focus | What to expect |
|---|---|---|
| Weeks 1–4 | Find your maintenance calories, set a 500–750 calorie daily deficit, get protein into every meal, start walking daily | Often a quicker drop early (part of it water), then it settles |
| Weeks 5–8 | Add 2 strength sessions a week, lock in a sleep routine, swap sugary drinks for water | Steadier loss of about 1–2 lbs a week |
| Weeks 9–12 | Re-check calories (your needs drop as you lose), build toward 150+ active minutes a week | Progress may slow; that’s metabolism adapting, not failure |
| Weeks 13–24 | Keep the habits that worked, adjust what didn’t, practice maintenance eating | The 25-pound mark lands somewhere in here for most people |
The foundation: a moderate caloric deficit
Weight loss still comes down to taking in fewer calories than you burn. Federal obesity guidelines suggest a deficit of 500 to 750 calories a day as a starting point (Jensen et al., 2013 AHA/ACC/TOS guideline). You may have heard that every 3,500 calories equals a pound. That’s a fine back-of-napkin number for the first few weeks, but NIH researchers showed it overestimates loss over time, because your body burns a bit less as you get lighter. That’s why progress naturally slows, and why the free NIH Body Weight Planner is a better tool than the 3,500 rule for setting your numbers.
A few guardrails that matter more than people expect:
- Don’t drop too low. Clinical guidelines generally land on about 1,200–1,500 calories a day for women and 1,500–1,800 for men, adjusted for body size and activity (Jensen et al., 2013). Very-low-calorie diets (under 800 a day) are meant only for medically supervised programs. Going too low makes it hard to get enough nutrients, and it tends to backfire through muscle loss and rebound eating.
- Know your maintenance calories first. The NIH Body Weight Planner estimates them from your age, height, weight, and activity, then shows the intake that gets you to your goal by a date you choose. It also flags it if your plan is too aggressive.
- Re-check every few weeks. As you lose weight, your maintenance calories drop too, so the deficit that worked at week one may need adjusting by week eight.
Prioritize protein
If I had to pick one food habit to start with, it would be protein. Protein blunts hunger more than carbs or fat, has a higher “thermic effect” (your body burns more calories digesting it), and — critically — helps preserve muscle while you’re in a deficit, which keeps your metabolism from slowing as much.
Aim for roughly 25–40 grams of protein per meal, prioritizing whole sources: chicken, fish, eggs, Greek yogurt, tofu, legumes, and lean beef. Breakfast is a good place to start. In one small study, a 35-gram-protein breakfast cut evening snacking compared with skipping breakfast (Leidy et al., 2013). For more on balancing protein with carbs and fat, see my guide to macronutrients. If you eat mostly plants, these plant-based protein tips help.
| Food | Portion | Protein |
|---|---|---|
| Greek yogurt | 3.5 oz (100g) | 10g |
| Eggs | 3 large | 19g |
| Lean beef (sirloin) | 3 oz | 26g |
| Canned fish (tuna/salmon) | 3.5 oz | 19g |
| Edamame | 1 cup | 18g |
Cut back on refined carbs and added sugar — don’t eliminate carbs

Refined carbohydrates — white bread, pastries, sugary drinks — spike blood sugar and drive the crash-and-crave cycle that makes a calorie deficit feel miserable. Swapping them for whole grains, legumes, and vegetables keeps you fuller for the same or fewer calories, without needing to cut carbohydrates altogether. My anti-inflammatory foods list is a good place to find swaps that work double-duty for blood sugar and overall health. If sugar cravings are your sticking point, my 7-day sugar detox plan breaks it down one day at a time.
Drink water instead of your calories
Swapping sugary drinks for water is one of the simplest changes you can make. According to the CDC, a 12-ounce regular soda has about 155 calories and an orange soda about 195. Cutting out two sodas a day trims roughly 2,100 calories a week. Water also supports satiety and exercise performance. I go deeper on exactly how much to aim for in how much water should you drink a day.
Move more — cardio and strength, not just one or the other
Diet drives most of the number on the scale, but exercise is what protects your muscle, your metabolism, and your long-term success. The CDC recommends at least 150 minutes of moderate activity a week (30 minutes, five days a week works) plus at least two days of muscle-strengthening. Keeping weight off may take more. NIDDK notes some people need over 300 minutes a week to maintain their loss. And if you’ve avoided creatine because of the weight-gain rumors, that one’s worth a second look.
- Cardio (walking, cycling, swimming) burns calories directly and supports heart health. Starting with a daily walking goal — 10,000 steps is a popular benchmark, though any consistent increase helps — is one of the most sustainable ways to begin.
- Strength training builds and preserves muscle, which burns more calories at rest than fat tissue does. This matters even more in a calorie deficit, when your body is more prone to burning muscle along with fat if you’re not lifting. New to weights? Start with my guide to strength training for women over 40. The beginner routine works at any age.
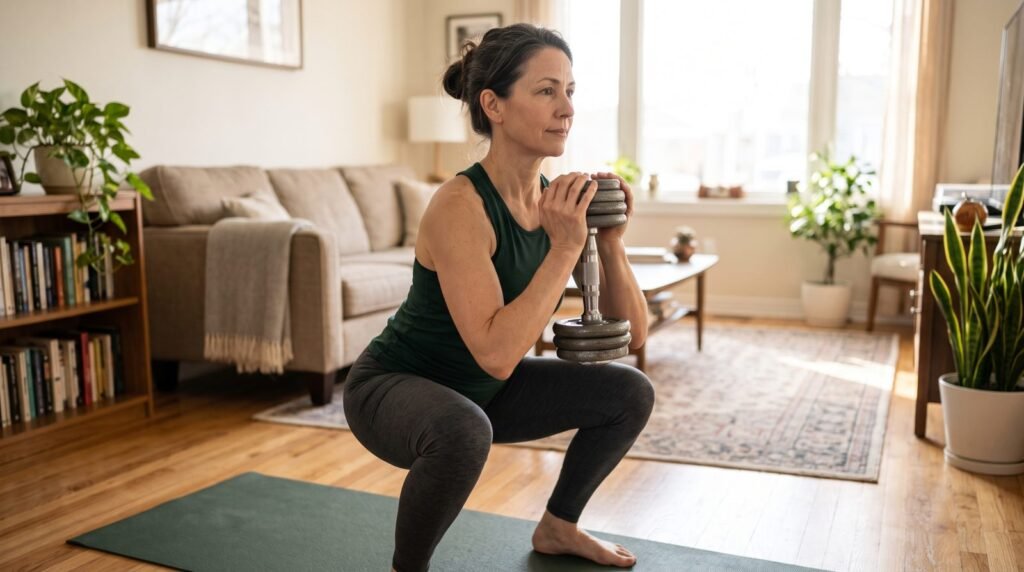
If you’re newer to structured exercise, my HIIT workout guide has a beginner-friendly plan that combines both.
Protect your sleep
This one surprises people. The CDC says adults need 7 or more hours a night, and regularly getting less is linked to obesity. Part of it is hormonal, since short sleep throws off ghrelin and leptin, the hormones behind hunger and fullness. Part of it is simpler: tired people eat more. A meta-analysis of sleep-restriction studies found people ate about 385 extra calories the day after a short night, without burning any more (Al Khatib et al., 2017). If sleep has been a struggle, my guides on how to fall asleep fast and magnesium for sleep can help.
Manage stress — cortisol works against you here
Chronic stress raises cortisol, and elevated cortisol is linked to increased appetite (especially for sugary, high-fat foods) and a tendency to store fat around the midsection. It’s an easy piece to overlook. Small daily downshifts like a short walk, slow breathing, or time away from your phone can help, and I go much deeper on this in cortisol and weight gain: how to lower cortisol naturally.
Eat mindfully, and watch for emotional eating
Eating while distracted — in front of a screen, rushing through a meal — is consistently linked to eating more without realizing it. Slowing down, and noticing when you’re eating from stress or boredom rather than hunger, is a skill that compounds over time. Two things help close that gap: a non-food outlet for stress (a walk, a call with a friend, a hobby) and a support system. In one classic study, people who joined a weight-loss program with friends were more likely to finish it (95% vs. 76%) and kept more weight off (Wing & Jeffery, 1999). For a gentle way to start, see my beginner’s guide to mindful eating.
A simple structure to build your plate around

You don’t need to track every gram forever. A simple visual guide works for most meals. It’s the same plate method the CDC uses: fill half a 9-inch plate with non-starchy vegetables, a quarter with lean protein, and a quarter with whole grains or starchy foods. Plan your shopping list ahead of time — it genuinely cuts impulse buys — and batch-prep what you can, since decision fatigue is one of the biggest reasons healthy plans fall apart by Wednesday. My meal prep strategies make the Sunday batch-cook a lot less of a chore.
A 2027 note on weight-loss medications (GLP-1s)
If you’ve been reading about Wegovy, Zepbound, or the new GLP-1 pills, you’re not alone. Here’s where things stand as of late 2026, in plain terms:
- The FDA has approved several prescription medications for chronic weight management, including the weekly injections semaglutide (Wegovy) and tirzepatide (Zepbound) (NIDDK).
- Two once-daily pills are now approved too: the Wegovy pill (oral semaglutide) in December 2025 (Novo Nordisk), and Foundayo (orforglipron) in April 2026 (FDA).
- They’re generally meant for adults with a BMI of 30 or higher, or 27 or higher with a weight-related condition like high blood pressure or type 2 diabetes. They’re approved for use alongside a reduced-calorie diet and more physical activity, not instead of them.
- Most people regain some weight after stopping, which is why the habits in this guide still matter (NIDDK).
- Be wary of cheap “compounded” or research-grade versions sold online. The FDA warns that these aren’t reviewed for safety, effectiveness, or quality.
For a 25-pound goal, many people won’t need medication at all. Whether it makes sense for you is a conversation for your doctor, not a blog post.
When to talk to your doctor first
Check in with a healthcare provider before you start if any of these apply:
- You have diabetes, heart disease, kidney disease, high blood pressure, or another ongoing condition, or you take medications (some affect weight or blood sugar).
- You’re pregnant, breastfeeding, or planning a pregnancy.
- You have a history of disordered eating.
- You’re thinking about a very-low-calorie diet, a weight-loss medication, or supplements.
- You’re losing weight without trying, or the scale won’t move despite consistent effort for several months.
The CDC also suggests asking your provider about referrals to a registered dietitian or a structured program. That support can make a big difference.
Frequently asked questions
How many pounds can I safely lose in a week?
Most guidance, including the CDC’s, points to about 1–2 pounds per week as the safe, sustainable range. Losing faster than that — like the “25 pounds in a week” searches you may have seen — isn’t realistic or safe; rapid drops that large are almost always water weight, not fat, and can come with real health risks.
How can I start creating a calorie deficit?
Estimate your maintenance calories, then aim for a deficit of 500–750 calories a day through a mix of eating a bit less and moving a bit more. The free NIH Body Weight Planner can do the math for you, and a tracking app makes it easier to stick to.
Why is protein so important for weight loss?
Protein keeps you fuller for longer, burns more calories to digest than carbs or fat, and helps preserve muscle while you’re losing weight — which keeps your metabolism from dropping as much as it would otherwise.
Do I need to cut carbs completely?
No. Reducing refined carbs and added sugar helps far more than eliminating carbohydrates altogether. Whole grains, legumes, and vegetables are carbohydrates too, and they support weight loss rather than working against it.
How does sleep affect weight loss?
Poor sleep disrupts the hormones that regulate hunger and fullness, and tends to increase overall calorie intake the next day. Protecting 7+ hours of sleep is one of the most underrated levers in a weight loss plan.
Can stress stop me from losing weight?
It can make it considerably harder. Chronic stress raises cortisol, which increases appetite and cravings and encourages fat storage around the midsection. Managing stress isn’t a nice-to-have here — it’s part of the plan.
Do I need a GLP-1 medication to lose 25 pounds?
Not usually. Most people can lose 25 pounds with a moderate calorie deficit, enough protein, regular activity, and better sleep. GLP-1 medications are prescription treatments for people who meet specific BMI and health criteria, and they work alongside those habits rather than replacing them. If you’re curious, ask your doctor whether you’re a candidate.
The bottom line

Losing 25 pounds the safe way, about 1–2 pounds a week over roughly 3 to 6 months, isn’t the fastest path. It is the one most likely to stick. Build your plan around a moderate calorie deficit, plenty of protein, regular movement that includes strength training, real sleep, and honest stress management. Small, consistent changes compound faster than most people expect. If you want help making these changes automatic, start with how to build healthy habits that actually stick. You’ve got this, and I’d love to be part of your journey there.
Want more realistic, evidence-based guidance like this? Join the newsletter for new guides as soon as they’re published.
Sources
- Centers for Disease Control and Prevention. Steps for Losing Weight. https://www.cdc.gov/healthy-weight-growth/losing-weight/index.html
- Centers for Disease Control and Prevention. Adult Activity: An Overview. https://www.cdc.gov/physical-activity-basics/guidelines/adults.html
- Centers for Disease Control and Prevention. Rethink Your Drink. https://www.cdc.gov/healthy-weight-growth/rethink-your-drink/index.html
- Centers for Disease Control and Prevention. About Sleep. https://www.cdc.gov/sleep/about/index.html
- Centers for Disease Control and Prevention. Diabetes Meal Planning (plate method). https://www.cdc.gov/diabetes/healthy-eating/diabetes-meal-planning.html
- National Institute of Diabetes and Digestive and Kidney Diseases (NIH). Body Weight Planner. https://www.niddk.nih.gov/bwp
- National Institute of Diabetes and Digestive and Kidney Diseases (NIH). Prescription Medications to Treat Overweight & Obesity. https://www.niddk.nih.gov/health-information/weight-management/prescription-medications-treat-overweight-obesity
- Hall KD, Sacks G, Chandramohan D, et al. Quantification of the effect of energy imbalance on bodyweight. Lancet. 2011;378(9793):826–837. https://pmc.ncbi.nlm.nih.gov/articles/PMC3880593/
- Jensen MD, Ryan DH, et al. Executive summary: Guidelines (2013) for the management of overweight and obesity in adults (AHA/ACC/TOS, with NHLBI Obesity Expert Panel). Obesity. 2014. https://doi.org/10.1002/oby.20821
- Al Khatib HK, Harding SV, Darzi J, Pot GK. The effects of partial sleep deprivation on energy balance: a systematic review and meta-analysis. Eur J Clin Nutr. 2017;71(5):614–624. https://www.nature.com/articles/ejcn2016201
- Leidy HJ, Ortinau LC, Douglas SM, Hoertel HA. Beneficial effects of a higher-protein breakfast on the appetitive, hormonal, and neural signals controlling energy intake regulation in overweight/obese, “breakfast-skipping,” late-adolescent girls. Am J Clin Nutr. 2013;97(4):677–688. https://pmc.ncbi.nlm.nih.gov/articles/PMC3718776/
- Wing RR, Jeffery RW. Benefits of recruiting participants with friends and increasing social support for weight loss and maintenance. J Consult Clin Psychol. 1999;67(1):132–138. https://pubmed.ncbi.nlm.nih.gov/10028217/
- U.S. Food and Drug Administration. FDA Approves First New Molecular Entity Under National Priority Voucher Program (Foundayo/orforglipron), Apr 1, 2026. https://www.fda.gov/news-events/press-announcements/fda-approves-first-new-molecular-entity-under-national-priority-voucher-program
- Novo Nordisk. FDA Approves Oral Wegovy Pill (Dec 22, 2025). https://www.novonordisk-us.com/media/press-releases/wegovy-pill-fda-approval-obesity.html
- U.S. Food and Drug Administration. FDA’s Concerns with Unapproved GLP-1 Drugs Used for Weight Loss. https://www.fda.gov/drugs/drug-alerts-and-statements/fdas-concerns-unapproved-glp-1-drugs-used-weight-loss
⚕️ Disclaimer: This article is for general informational and educational purposes only and is not a substitute for professional medical advice, diagnosis, or treatment. Always consult a qualified healthcare provider before making changes to your diet, exercise, supplement, or wellness routine. Read our full medical disclaimer.




[…] How to Lose 25 Pounds: A Realistic, Safe Plan That Lasts […]
[…] How to Lose 25 Pounds: A Realistic, Safe Plan That Lasts […]
[…] Intermittent fasting (IF) has become a big trend in health and wellness. It’s chosen by people wanting to lose weight, get smarter, and improve heart health. Unlike other diets that focus on what to eat, IF cares more about when you eat. This makes it a simple and flexible way to manage your weight by fasting and then eating — and it can slot neatly into a broader realistic plan to lose 25 pounds. […]
[…] Weight Management: While not a weight-loss strategy per se, mindful eating has helped me maintain a healthy weight by preventing overeating and fostering a balanced approach to food — it’s also one pillar of my realistic weight-loss plan. […]